for those looking for a compendium of mask studies this set from swiss policy research looks useful and has some good links and discussion.

also attaching 2 past debunkings of widely disseminated US studies that health officials have attempted to

first, the kansas study spread by CDC and so many "twitterdocs" and politicians.

it's a master class in cherry picking and misusing data through truncation.

the data proving it was false was widely available at the time it was published.

https://t.co/qY66ZaNnsn
also the mass general study, a classic of the "sun-dance" variant: use no control group and then presume that any action undertaken was the result of some thing you did.

ignore the fact that the whole rest of (unmasked) massachusetts got the same result

https://t.co/IBVypJbjPI
the fact that CDC has been spreading studies like these and using them alongside flimsy lab bench experiments with no clinical outcomes or even real world measurement speaks poorly of both CDC & the evidence for masks

the good studies do not support use

https://t.co/viMzUDYm29
and lab bench droplet projection studies are meaningless.

it's one tiny aspect of a large system and may actually be counterproductive if masks are nebulizing droplets and making virus more aerosol in spread and more deeply penetrating.

https://t.co/nFD9onkjrn
is this the case and can it dominate droplet spread reduction? maybe. we don't really know. does it account for edge leaks and the benefits of coughing into a hand or handkerchief?

there are 1000 variables. this is why you need actual clinical outcomes studies not lab models
anyone trying to pass those lab models off as proof is essentially arguing "hey, it killed cancer in a petri dish, it will work in your body!" then you drink bleach. oops.

this is not the way actual science is done and it's embarrassing to watch it get passed off as such.
masks are a visible in-group talisman with little or no real scientific backing.

they are playing the role of tribal signifier rooted in superstition and superstition.

calling that science is just doubling down on the same.

i suspect this is why the debate is so rancorous.
no one likes having their holy talismans demeaned or demonstrated to be false and tribes rally around them when challenged.

attacking masks is attacking a religion, not a scientific practice.
such secular religions are tricky. the converts do not realize it's religious in nature. their very dogma is that "it's science"

but it's not. science asks questions and addresses data

this is self delusion about one's own superstitions reinforced by tribal virtue signaling.
the end result is that almost nobody can really convince anybody to change their mind.

but take a deep breath and take a dispassionate look at the data. it may help.

i began with the presumption that masks ought to work.

then i looked for data.

i presumed it was a slam dunk.
but it's not. at all. the data for masks is limited, sparse, situational, and mostly poorly gathered

many of the studies are outright junk

as i read through the literature, it seemed that the better the study design, the less efficacy it showed

ultimately, it changed my mind
and i came to the view that masks look to have no material effect and are likely causing more harm than good even before adding in the psychological factors.

try it yourself. there are lots of studies.

hold your priors loosely, be open to data, and read them.
if you are not willing to do that, (and let's face it, most are not) then you really need to stop claiming to be "on the side of science" because that's what science is.

it's open minded questioning, not regurgitation of dogma and submission to credentialism.

food for thought.

More from el gato malo

did you consider checking the facts before buying into such hysterical claims?

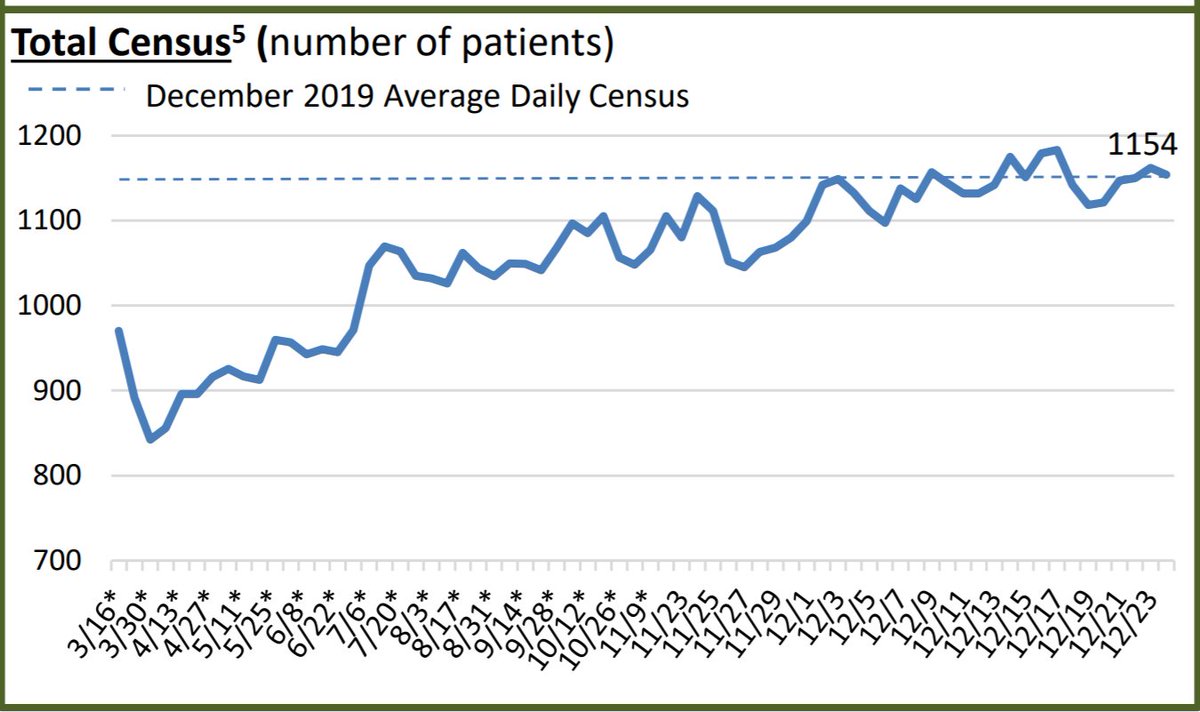
this is LA department of health services hospital census. it's essentially identical to the levels from last year.

the media have had a severe tendency to overstate these issues. https://t.co/ktTPIbKcdQ


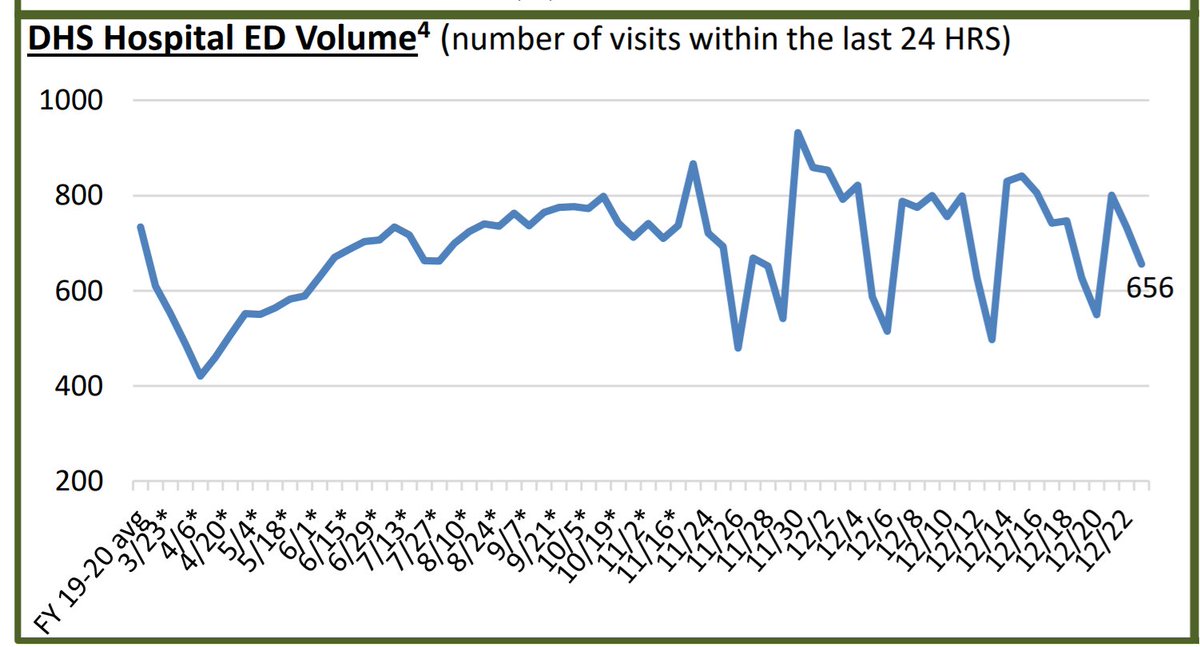
as you can see, visits to emergency departments have been quite stable for 4 months.


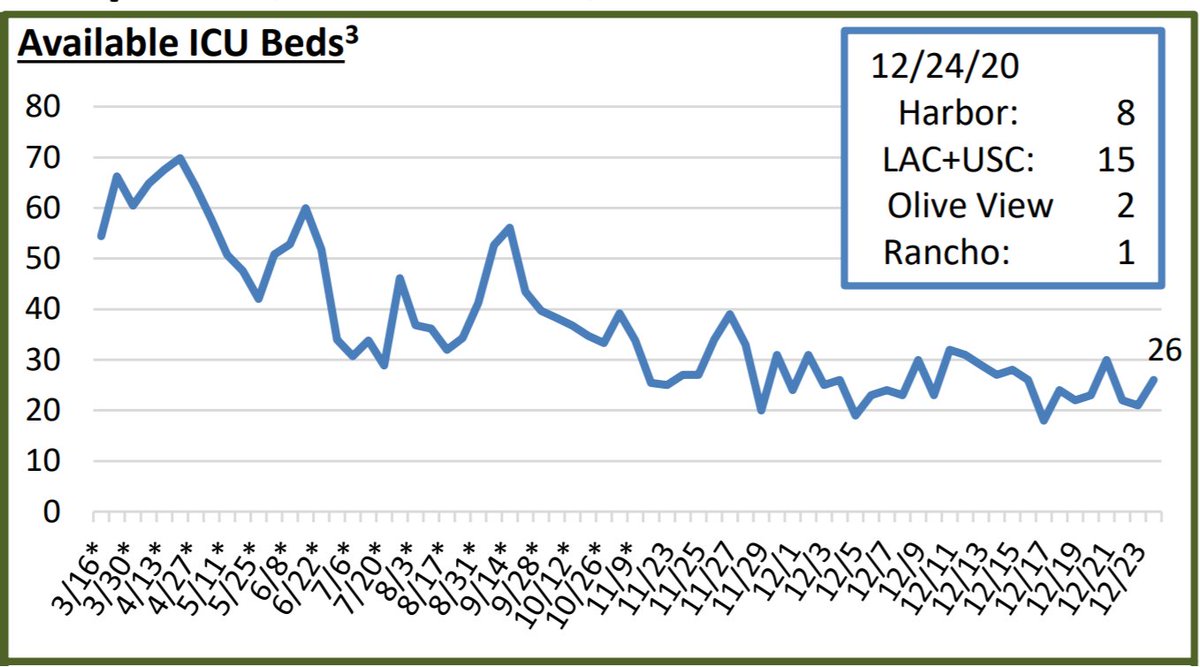
and ICU bed availability has been flat for the whole month of december.

keep in mind that 90-100% ICU capacity is normal this time of year and that all ICU's must be able to flex to 120% (by federal law) and most can hit 150%.


and if you will not take my word for it, just ask the CEO's of the hospitals in texas everyone was so breathless about this summer.

they were not worried. and they were


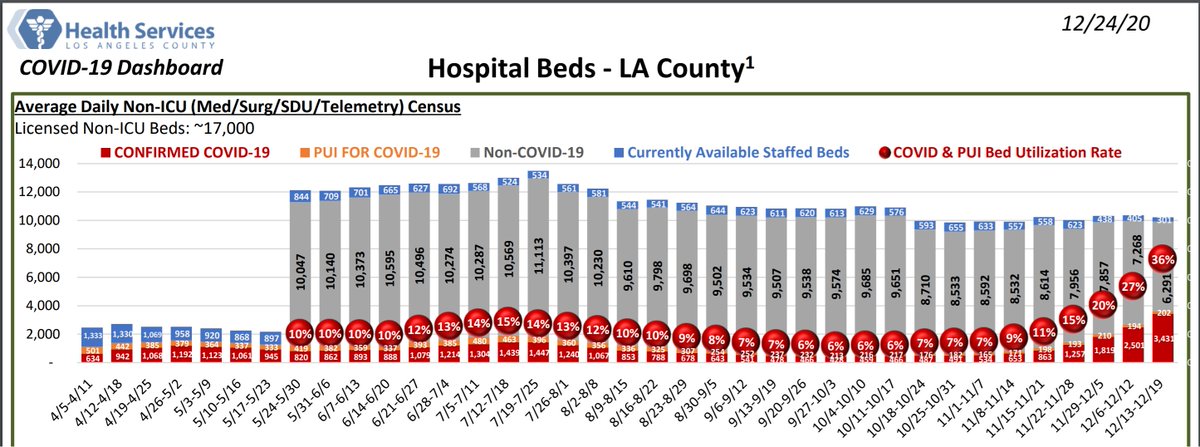
hospital census in LA seems to be about 3000 patients below where it was in july.

this seems to imply a drop in staffed beds which, contrary to the narrative is not from "exhaustion" but rather from people being laid off or staying home because kids are not in school.
global health policy in 2020 has centered around NPI's (non-pharmaceutical interventions) like distancing, masks, school closures

these have been sold as a way to stop infection as though this were science.

this was never true and that fact was known and knowable.

let's look.


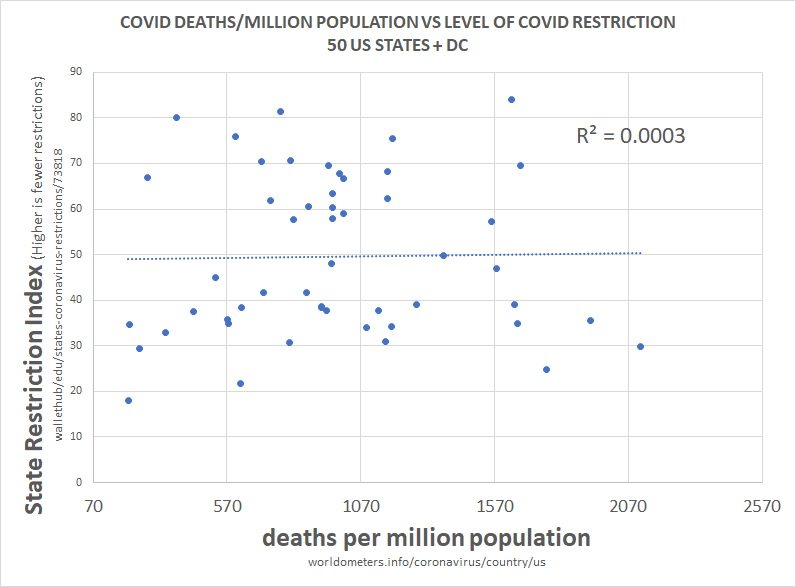
above is the plot of social restriction and NPI vs total death per million. there is 0 R2. this means that the variables play no role in explaining one another.

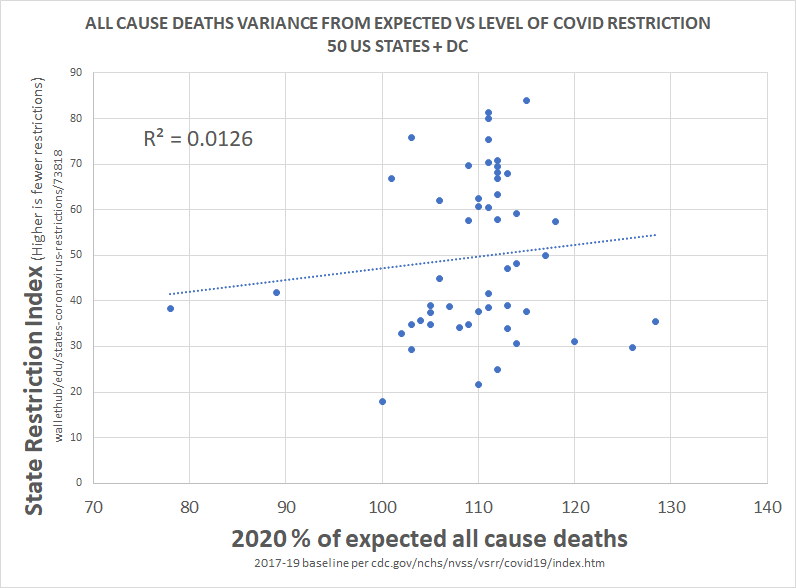
we can see this same relationship between NPI and all cause deaths.

this is devastating to the case for NPI.


clearly, correlation is not proof of causality, but a total lack of correlation IS proof that there was no material causality.

barring massive and implausible coincidence, it's essentially impossible to cause something and not correlate to it, especially 51 times.

this would seem to pose some very serious questions for those claiming that lockdowns work, those basing policy upon them, and those claiming this is the side of science.

there is no science here nor any data. this is the febrile imaginings of discredited modelers.

this has been clear and obvious from all over the world since the beginning and had been proven so clearly by may that it's hard to imagine anyone who is actually conversant with the data still believing in these responses.

everyone got the same R
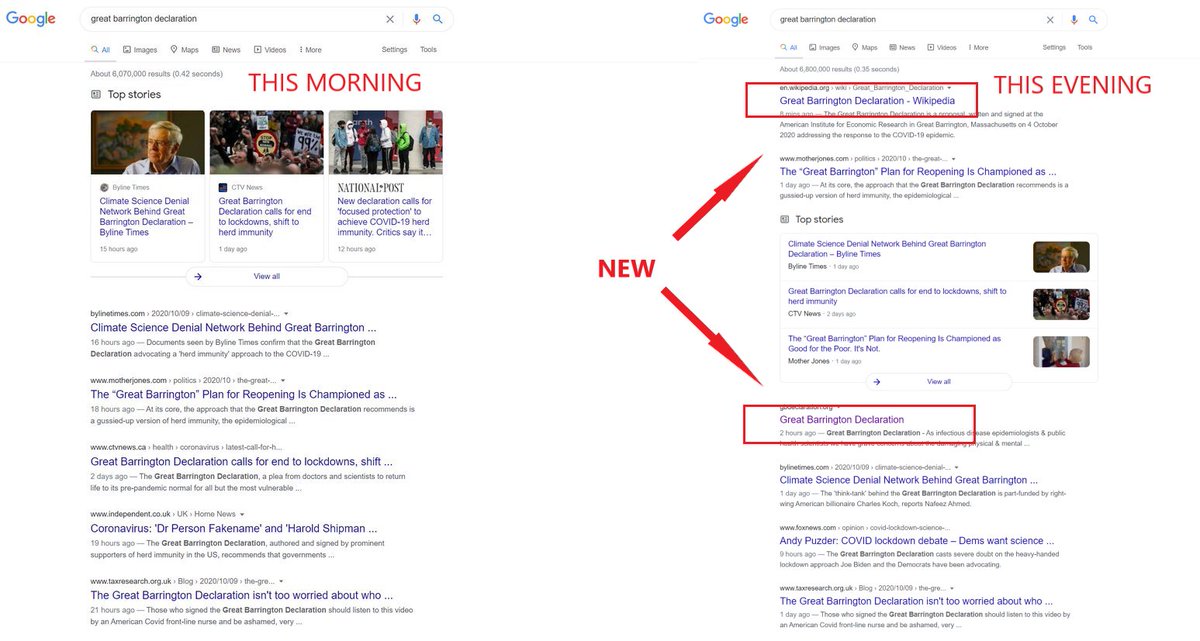
google censorship of great barrington declaration: update.

this morning, there was no link to it in a direct google search.

now, there is.

could this be because certain internet felines noticed this and @chiproytx and @tedcruz helped call them out on this?

we may never know.


but i'd like to think so.

the google page is still a mess. it's still mostly fringe publication hit pieces and conspiracy theories.

when "mother jones" is your top media result for a science search, well, that says it all, doesn't it?

yikes.

i mean, why would we trust THESE people instead of a reporter at one of the most partisan rags on earth? oh, wait..

they are not being censored for being wrong. they're being censored for being right and being credible

they're censored because the other side cannot rebut them


and that is simply not a thing we can or should tolerate, especially not in a search engine.

so remember this. look for it in the future. demand primary sources.

use other search engines.

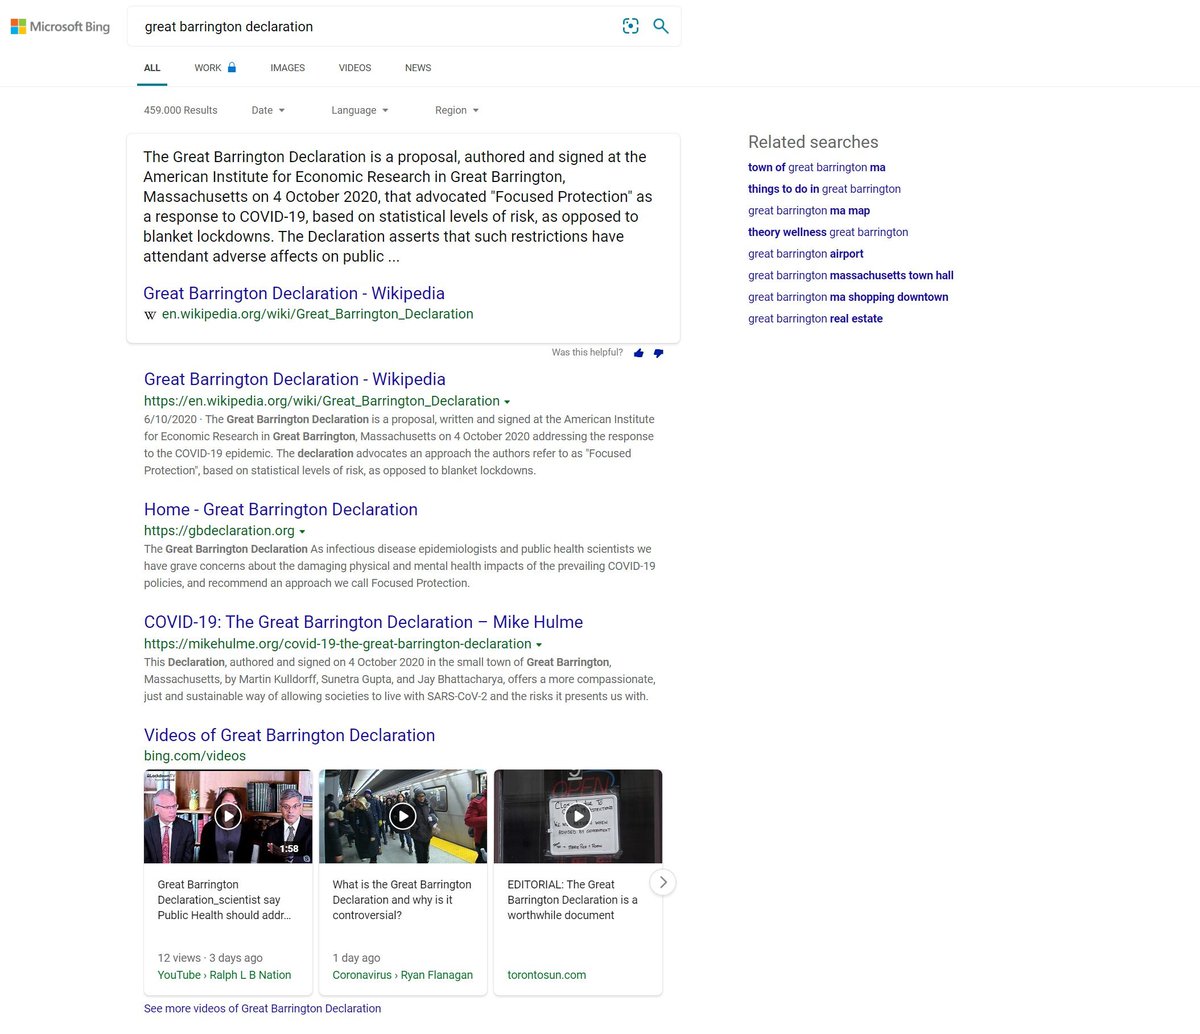
bing seems to be seeking to inform, not to inflame and mislead.


if you missed it, the original thread was here:

(and yes, lots of people duplicated my finding this morning)

i'd be curious to see what they are all seeing

More from Society

I've seen many news articles cite that "the UK variant could be the dominant strain by March". This is emphasized by @CDCDirector.

While this will likely to be the case, this should not be an automatic cause for concern. Cases could still remain contained.

Here's how: 🧵

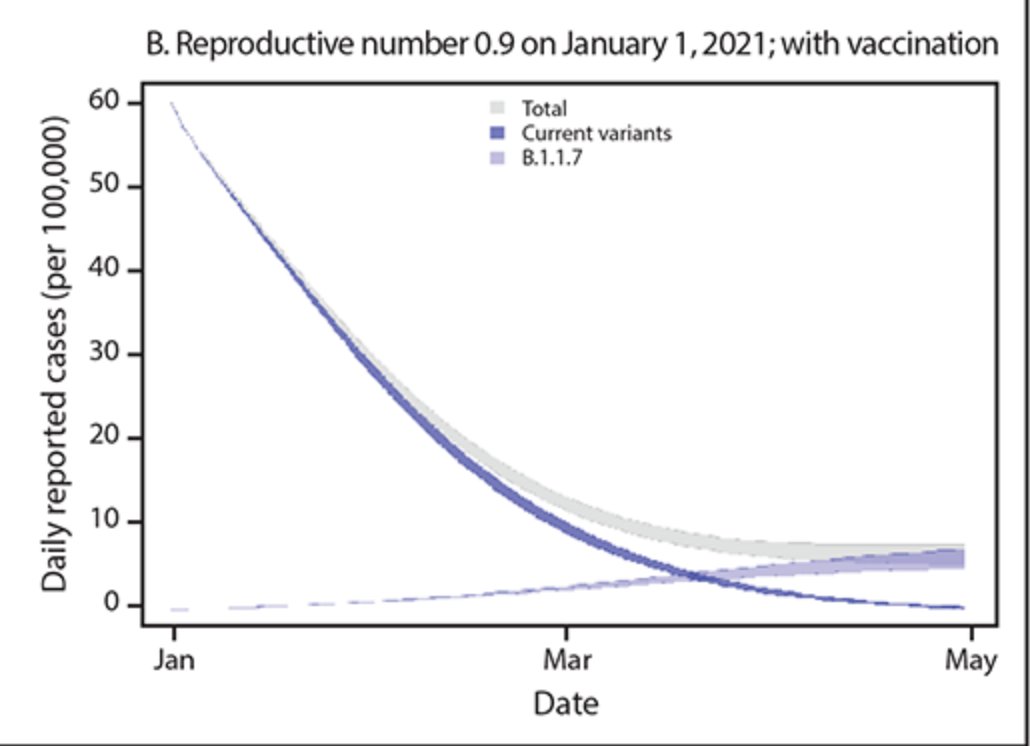
One of @CDCgov's own models has tracked the true decline in cases quite accurately thus far.

Their projection shows that the B.1.1.7 variant will become the dominant variant in March. But interestingly... there's no fourth wave. Cases simply level out:

https://t.co/tDce0MwO61


Just because a variant becomes the dominant strain does not automatically mean we will see a repeat of Fall 2020.

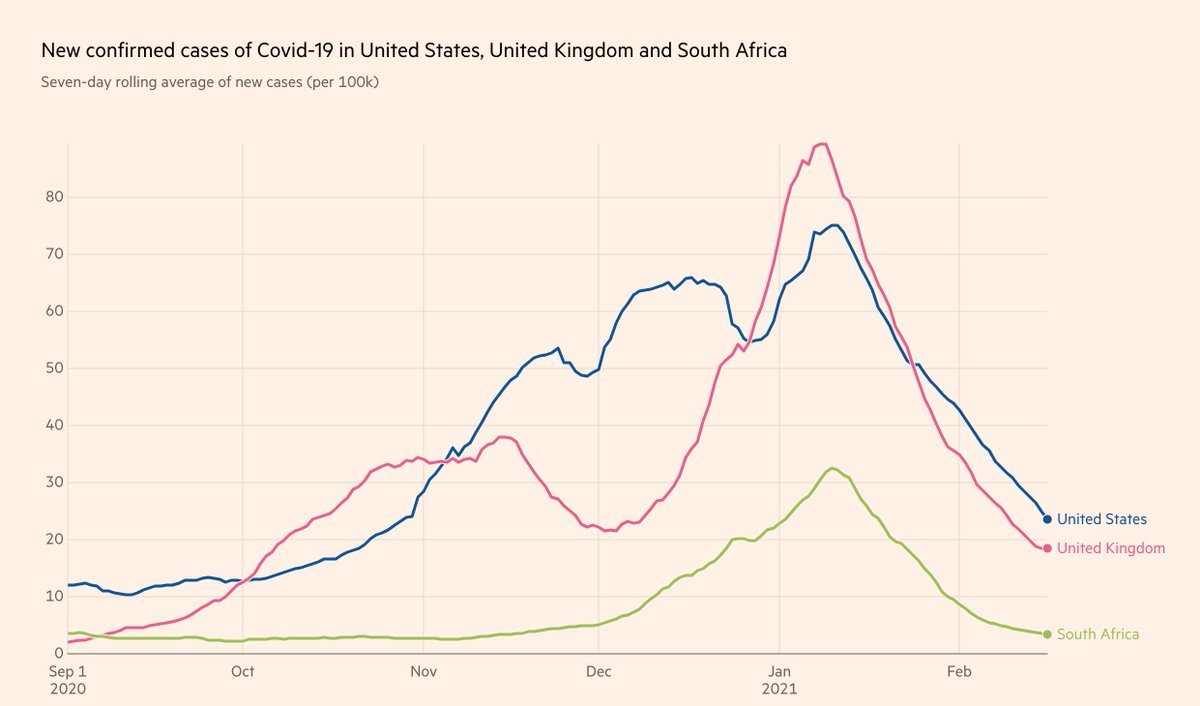
Let's look at UK and South Africa, where cases have been falling for the past month, in unison with the US (albeit with tougher restrictions):


Furthermore, the claim that the "variant is doubling every 10 days" is false. It's the *proportion of the variant* that is doubling every 10 days.

If overall prevalence drops during the studied time period, the true doubling time of the variant is actually much longer 10 days.

Simple example:

Day 0: 10 variant / 100 cases -> 10% variant
Day 10: 15 variant / 75 cases -> 20% variant
Day 20: 20 variant / 50 cases -> 40% variant

1) Proportion of variant doubles every 10 days
2) Doubling time of variant is actually 20 days
3) Total cases still drop by 50%

You May Also Like